

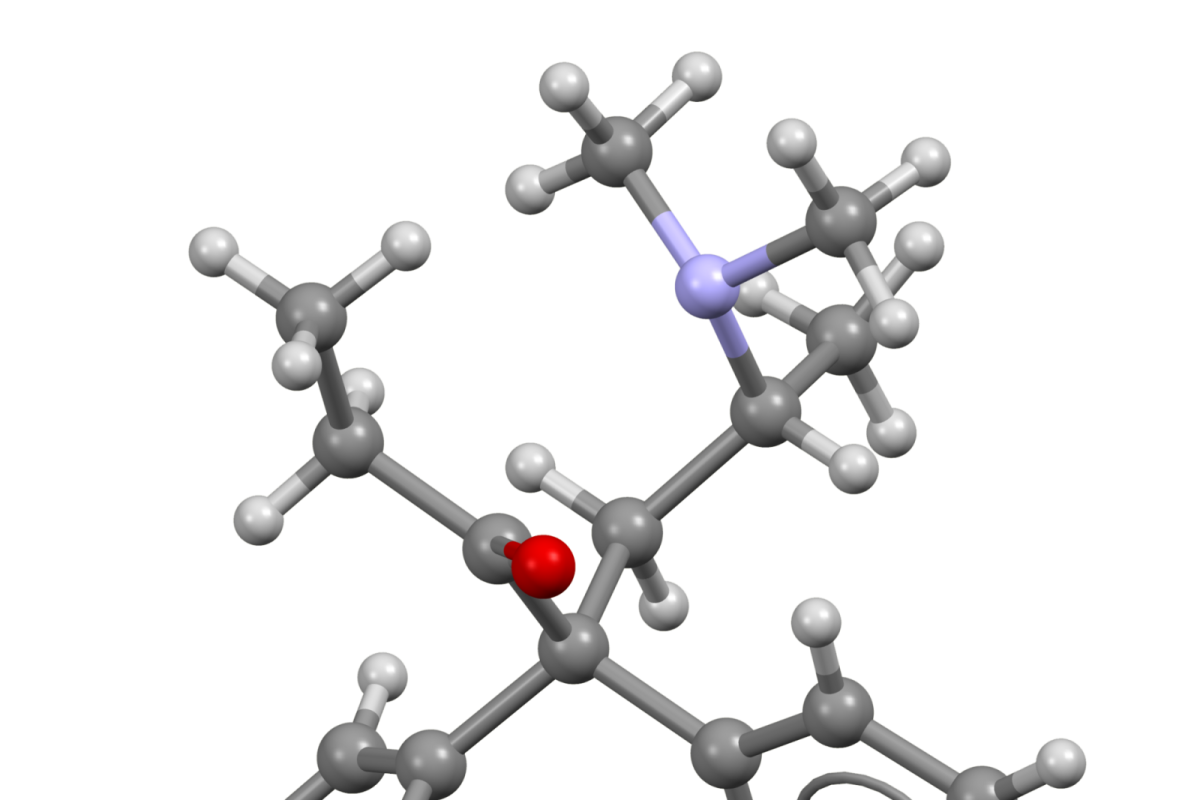
Methadone represents one of the fundamental pillars in modern pharmacology for managing substance use disorders. As a long-acting opioid agonist, it has enabled a transition from purely abstinence-based models toward comprehensive strategies focused on harm reduction and social recovery. Its implementation marked a turning point in the healthcare management of opioid addictions, offering a therapeutic alternative that balances symptom control with the preservation of the patient’s vital functionality.
In brief
- Mechanism of action: Methadone acts as an opioid agonist, eliminating withdrawal symptoms and cravings without producing intense euphoria.
- Historical evidence: Classic studies demonstrate a reduction of over 80% in illicit consumption and associated criminal activities.
- Epidemiological impact: The widespread adoption of maintenance programs contributed decisively to a drastic drop in new HIV infections among opioid users.
- Clinical management: Therapeutic success depends on removing administrative barriers, allowing for flexible dosing, and keeping the patient within the healthcare system.
- The cessation challenge: Discontinuation requires a gradual process due to the drug’s long half-life; emerging methods like ibogaine are being studied to facilitate this final step.
Pharmacological Foundations and Historical Evolution
Initially synthesized in Germany in 1937, methadone evolved from an obscure analgesic outside of German-speaking regions to a global tool following World War II. Its introduction to the US market under the trade name “Dolophine” (from the Latin dolor, pain) in 1947—without any erroneous political connotation as has sometimes been speculated—laid the groundwork for its clinical use.
The true paradigm shift occurred in the late 1950s and early 60s. Pioneer researchers like Dole and his collaborators demonstrated that the pharmacological use of methadone could effectively replace illicit heroin use. This approach was based on clear premises: eliminating the need to seek doses, suppressing withdrawal symptoms, and allowing for a normalized, functional life.
International adoption was progressive but decisive. While Nordic countries like Sweden and the United Kingdom initiated programs in the late 60s, Spain was slow to integrate this tool into its therapeutic arsenal until the late 1980s. This delay had serious health consequences, reflected in HIV infection rates that were disproportionate compared to other European countries that adopted the model earlier.
Criteria for Efficacy and Harm Reduction
To be considered a valid tool in the treatment of opioid dependence, any substance must meet strict requirements. Methadone satisfies these criteria by eliminating the pull of heroin’s immediate euphoric effects while blocking withdrawal impulses. Unlike illicit use, its controlled administration carries no risk of acute overdose if the established dosage is respected, and it allows patients to maintain their work, academic, and family responsibilities.
An anecdotal testimony illustrates this transformation well: a patient who, after multiple failed attempts in traditional centers, found stability with methadone. It allowed him to reintegrate socially and manage his family and work life without the need to constantly consume to avoid the physical or psychological discomfort of withdrawal syndrome.
Epidemiological Evidence and HIV Control
The efficacy of methadone is not merely anecdotal; it is supported by compelling statistical data. Retrospective studies conducted in New York in the early 80s showed that after the start of mass maintenance programs, drug-related arrests and the incidence of hepatitis decreased drastically. In Spain, this model demonstrated an exceptional capacity to curb the HIV epidemic among intravenous drug users.
According to World Health Organization data cited in analyses after 2013, the number of new HIV infections in the Spanish heroin-using population dropped significantly following the expansion of methadone programs. The key to success was not just the drug, but administrative flexibility: allowing patients to take doses home and avoiding premature expulsion due to difficult behaviors or sporadic residual use.
The Challenge of Therapeutic Discontinuation
Despite its indisputable efficacy in maintenance, methadone is not a panacea. Its use implies maintaining a controlled pharmacological dependence, which raises an ethical and clinical dilemma: when is it time to try to stop? Discontinuation must always be voluntary and planned.
The weaning process presents difficulties inherent to the drug’s long half-life. An abrupt reduction in dosage causes severe withdrawal syndrome, which leads many patients to remain stuck on minimal doses for years or decades. This situation can create a sense of therapeutic entrapment, where the patient feels there is no exit toward total abstinence.
Currently, alternative methods to facilitate this final step are being researched and applied, such as the use of ibogaine in controlled contexts. However, it is essential to remember that any cessation strategy must be supervised by qualified healthcare professionals, adapting to the patient’s individual clinical history.
Conclusion: Toward Comprehensive Medicine
Methadone has proven to be an indispensable instrument in the fight against opioid addictions. Its value transcends symptomatic relief; it is a public health tool that saves lives, reduces criminality, and prevents epidemics. The future challenge lies not in questioning its utility, but in optimizing maintenance programs to facilitate safe transitions toward abstinence when the patient decides to do so.
At Psiconáutica.org, we advocate for an approach based on scientific evidence and clinical compassion. Recognizing that recovery is a non-linear process, where stabilization is sometimes needed before moving forward, is essential to offering dignified and effective care. Methadone, far from being an end in itself, is the safe bridge toward a life free of compulsive addictions.


