

In brief
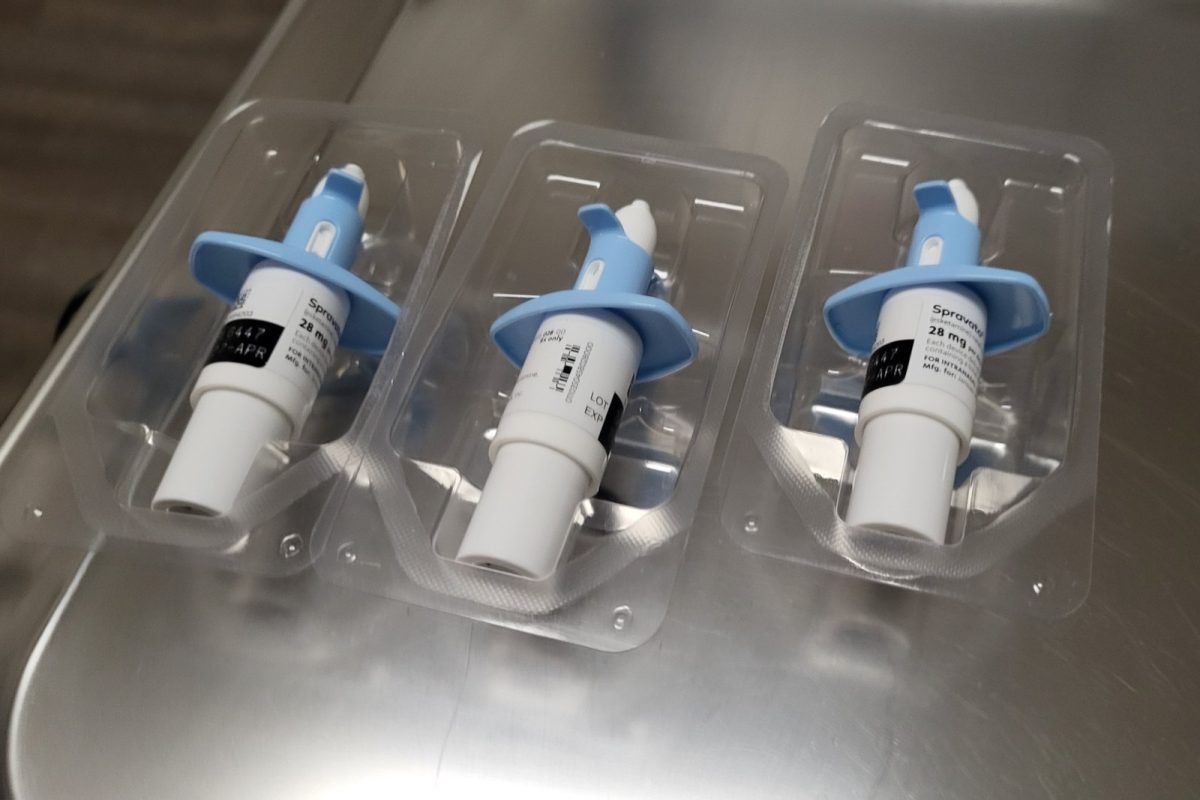
- A team at the Mayo Clinic (Minnesota) reviewed seven years of medical records from 104 patients treated with intravenous ketamine or intranasal esketamine for treatment-resistant depression.
- Only three individuals showed notable elevations in liver enzymes, and the authors proposed alternative explanations, without experimentally ruling out causality.
- The authors conclude that at typical therapeutic doses, their data do not support universal monitoring in asymptomatic patients, while clinical judgment and pre-existing vulnerability remain relevant.
A cohort study published on July 28 in the journal Journal of Clinical Psychopharmacology provides one of the most comprehensive datasets to date on what happens to the liver in individuals receiving ketamine or esketamine as a prolonged psychiatric treatment. The answer, with some caveats, is reassuring: no signs of drug-induced liver injury were observed.
What was measured
The team, led by psychiatrist Balwinder Singh, reviewed medical charts from the Mayo Clinic’s ketamine service between August 2017 and August 2024. Of the 104 patients with treatment-resistant depression included, 74 had liver enzyme tests, and 51 had follow-up measurements after starting treatment, with paired before-and-after comparisons available only in differing subsets for each marker. Subanesthetic intravenous ketamine (0.5 mg/kg) was administered to 78% of patients, while 22% received intranasal esketamine at approved doses. The median age was approximately 51 years, and the text and table disagree on sex distribution, so that detail cannot be treated as resolved.
The data
When comparing changes in transaminases (AST and ALT), alkaline phosphatase, and bilirubin before and after starting treatment, the researchers found no statistically significant trends across any of these markers: monthly fluctuations averaged under 0.3%. Only three patients—5.9% of those with follow-up testing—exhibited enzyme levels twice or more above the upper limit of normal, and in all three instances, an alternative explanation was documented in their medical history: pre-existing steatosis in one case and alcohol-withdrawal hospitalizations in two others. Authors considered treatment attribution unlikely; causality was not experimentally excluded.
What this means
It is important to place these findings in perspective. This is a single-center, retrospective study with a relatively small, homogeneous cohort—limitations the authors themselves acknowledge: transient, asymptomatic enzyme spikes could have gone undetected if blood tests were not ordered at that exact moment. Nor does it shed light on recreational ketamine use at much higher doses and frequencies, where biliary and bladder toxicity is well-documented and represents a very real risk for anyone using it outside a clinical setting. What it does provide is concrete real-world evidence on the doses prescribed in ketamine and esketamine therapy for treatment-resistant depression: at therapeutic doses and under clinical supervision, no significant change in those markers was detected, without ruling out unobserved abnormalities. The authors call for larger, prospective studies before drawing definitive conclusions, but their interpretation of monitoring asymptomatic patients does not replace clinical judgment or cover every form of hepatic vulnerability. For anyone considering this treatment—or using the compound independently—understanding these findings, and their limitations, is vital for making informed decisions, which forms the cornerstone of any genuine harm reduction strategy. As for the other side of long-term monitoring, we previously covered how France tightened surveillance on long-term ketamine use.
Source
- Singh B, Leung JG, Pazdernik VK, Kung S, Vande Voort JL. Hepatic Safety of Ketamine and Esketamine for Treatment-Resistant Depression: A Real-World Cohort Study. Journal of Clinical Psychopharmacology, July 28, 2026.
Educational content written from a harm reduction perspective and with respect for individual freedom. It is not a substitute for advice from a healthcare professional and is not intended to encourage or condemn any drug use.

