

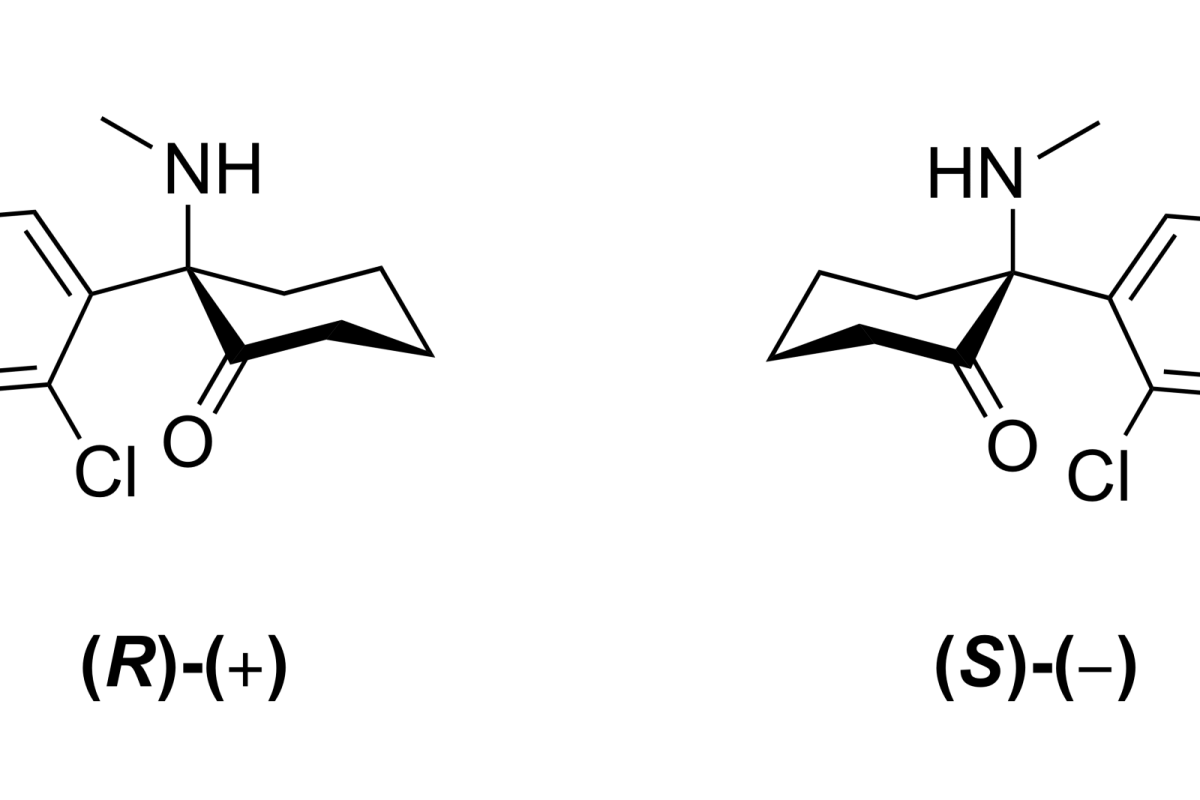
In brief
- Ketamine is a dissociative anesthetic (an NMDA receptor antagonist) with two distinct contexts of use: one clinical and structured, the other recreational and self-managed.
- In its medical form, esketamine (Spravato) is approved by the EMA and FDA for treatment-resistant depression and is administered under medical supervision.
- Repeated recreational use can be associated with bladder and kidney issues (ketamine-induced uropathy), effects on memory, and respiratory risks when combined with other depressants; understanding these helps in making informed decisions and practicing self-care.
Ketamine lives a double life: it is a medication with decades of history in operating rooms and, more recently, in psychiatry, but it is also a substance with increasingly common recreational use. Understanding what separates one context from the other helps to evaluate its effects and risks with rigor, without drama, and without idealization.
A dissociative anesthetic with two lives
Ketamine was developed decades ago as an anesthetic, a less toxic alternative to phencyclidine (PCP). It acts primarily by blocking the NMDA glutamate receptor, which produces analgesia, anesthesia, and, at lower doses, its characteristic dissociative effects: a sensation of disconnection from the body and the environment, distortion of light and sound perception, and, at high doses, the so-called “k-hole,” a state of profound detachment from reality. That same mechanism explains both its medical interest and its recreational appeal, and why it is wise to know it well before use.
Clinical use: a highly structured framework
The most discussed modern medical use is esketamine, a derivative marketed as Spravato in the form of a nasal spray. The FDA approved it in 2019 for treatment-resistant depression and, in 2025, expanded its use as monotherapy. In Europe, the European Medicines Agency (EMA) authorized it for adults with treatment-resistant major depression who have not responded to at least two antidepressants, always in combination with an SSRI or an SNRI, and also to rapidly reduce depressive symptoms in a psychiatric emergency.
The essential difference from recreational use lies in the context and control. Esketamine is administered in a clinic or office, with the accompaniment of a healthcare professional who measures blood pressure before and after, as it can raise it, and with the dose adjusted on a case-by-case basis. Due to its potential for dissociation, it is dispensed within specific programs. As context: in Spain, ketamine is a controlled substance, and its use outside of medical indications is not regulated; research into other applications remains, for the most part, preliminary.
Recreational use: effects and risks
Outside of the clinical environment, without measured doses or monitoring, the effect profile changes. In the short term, dizziness, nausea, blurred vision, difficulty speaking, or changes in blood pressure and heart rate may occur. The point most worth keeping in mind is respiratory depression, especially when combining ketamine with other depressants such as alcohol, opioids, benzodiazepines, or GHB. This is not a minor detail: calls to poison control centers in the U.S. regarding ketamine-associated problems increased by 81% between 2019 and 2021.
Repeated use adds effects that may take time to manifest. The most characteristic is ketamine-induced uropathy: its metabolites, such as norketamine, damage the cells of the urothelium, promote inflammation and fibrosis, and cause urinary symptoms similar to those of an infection. In advanced cases, bladder and kidney damage can become difficult to reverse and may require dialysis. Abdominal pain (“k-cramps”), effects on memory, low mood, and, at high doses or in vulnerable individuals, psychotic episodes are also described. Evidence also points to a potential for dependence, with tolerance and compulsive use. Knowing these limits allows one to manage frequency and dosage.
Harm reduction
Anyone who decides to use ketamine can significantly reduce risks with simple measures, and they deserve that information without lectures. The most important is not to mix it with other depressants (alcohol, opioids, benzodiazepines, GHB) due to the risk of respiratory arrest, and to avoid using it alone: having someone nearby makes the difference if something goes wrong. Due to dissociation and loss of coordination, it is not the time to drive or operate machinery. Taking care of set and setting—mood, company, and a safe environment—completely changes the experience.
To limit bladder damage, clinical evidence suggests that good hydration and frequent urination reduce the bladder’s exposure to ketamine and its metabolites; the risk grows with high doses, frequent consumption, and prolonged use, so spacing out use provides protection. In the presence of persistent urinary symptoms (pain when urinating, urgency, blood), it is advisable to seek medical attention promptly and be honest about consumption: early detection and a sustained break are what prevent the most serious complications, and a professional who treats patients with respect will make it easy. Drug checking and harm reduction services help to understand purity and composition and provide guidance on risks. And if consumption starts to become difficult to control, asking for help is not a failure, but a lucid way of taking care of yourself.
Sources
- National Institute on Drug Abuse (NIDA). Ketamine. NIDA, 2024.
- European Medicines Agency. Spravato (esketamine): EPAR. EMA, 2024.
- Recognition and Management of Recreational Ketamine-Induced Uropathy. The Primary Care Companion for CNS Disorders, 2024.
Educational content written from a harm reduction perspective and with respect for individual freedom. It is not a substitute for advice from a healthcare professional and is not intended to encourage or condemn any drug use.


